Emergency Dentist FAQs for First-Time Patients

Dental emergencies have a way of disrupting more than your schedule. They affect sleep, concentration, meals, work, and sometimes your confidence the moment you open your mouth to speak. For someone who has never needed urgent dental care before, the uncertainty can feel worse than the tooth itself. Is this serious enough to call? Will a dentist see me the same day? What if the pain starts at night, or the swelling appears out of nowhere, or a filling drops out on a holiday weekend?
Those questions are common, and they are reasonable. First-time patients often assume an Emergency Dentist only treats dramatic injuries, such as a knocked-out tooth after a sports accident. In practice, urgent dental visits cover a much wider range of problems, from severe toothaches and cracked teeth to gum abscesses and infections that have started to spread. The key issue is not whether the problem looks dramatic. It is whether waiting is likely to worsen pain, damage the tooth, or put your health at risk.
What follows is a practical guide to the questions people ask most often before that first urgent visit. It is written for the patient who is trying to make a good decision quickly, without guessing and without downplaying symptoms that deserve attention.
What actually counts as a dental emergency?
A dental emergency is any oral health problem that needs prompt evaluation because pain is significant, function is impaired, bleeding is hard to control, or infection or trauma may threaten the tooth or surrounding tissues. Some cases are obvious. A tooth that has been knocked out, a jaw injury, or uncontrolled bleeding after an extraction clearly needs immediate care. Other cases are less dramatic but still urgent. A throbbing tooth that keeps you awake, facial swelling near a painful tooth, a broken crown exposing sensitive tooth structure, or a sharp crack that makes biting impossible all deserve a same-day call.
One point that surprises first-time patients is that pain severity does not always match seriousness. A small crack can hurt badly when you bite, while a deeper infection may begin with a dull ache and mild swelling before escalating quickly. Likewise, some problems that look minor in the mirror can hide substantial trouble under the gumline or inside the tooth.
A good working rule is simple. If the issue is rapidly getting worse, interfering with eating or sleeping, accompanied by swelling or fever, or tied to trauma, do not wait for your next routine appointment. Call an Emergency Dentist.
When should I call an Emergency Dentist instead of going to the hospital?
This is one of the most important distinctions to understand. Dentists are the right call for most tooth and gum emergencies because they can diagnose the source and treat it directly. Hospitals are essential when the problem involves your overall safety, breathing, severe facial trauma, or infection that appears to be spreading beyond the mouth.
Use this quick guide if you are unsure:
- Call an Emergency Dentist for severe toothache, a broken or cracked tooth, a lost filling or crown, a knocked-out tooth, a loose adult tooth, localized gum swelling, or bleeding that seems to come from the tooth or gums.
- Go to the emergency room for trouble breathing, difficulty swallowing, rapidly spreading swelling into the face or neck, heavy bleeding that does not slow with pressure, high fever with dental swelling, or significant facial injury after an accident.
- If you suspect a broken jaw, head injury, or loss of consciousness, skip the dental office and seek emergency medical care first.
- If it is after hours and you are not sure which setting is appropriate, call the Emergency Dentist anyway. Many offices have an after-hours line and can help you decide safely.
In day-to-day practice, the most concerning sign is swelling that changes your ability to swallow, speak normally, or breathe comfortably. Dental infections can spread into deep facial spaces. That is not common, but it is not something to monitor at home while hoping the pain eases.
Can I wait until morning if the pain started overnight?
Sometimes yes, sometimes no. A mild toothache that responds to over-the-counter pain relief and is not associated with swelling, fever, or trauma can often wait until the office opens. Many first-time patients do exactly that and are fine. A sharp pain from biting into something hard, or a chipped tooth without major pain, usually allows for a next-morning call.
Night pain that is intense, persistent, and pulsing is different. If you cannot sleep despite medication taken as directed, or if swelling is developing, you should contact the on-call number if one is available. Dental pain tends to feel worse at night because you are still, distracted by nothing else, and blood flow dynamics can increase pressure in an inflamed tooth. That does not automatically mean disaster, but it is a clue that the tissue inside the tooth may be significantly inflamed or infected.
Many urgent calls happen between 10 p.m. And 2 a.m. After people have spent the whole evening trying to outlast the discomfort. If you are pacing the kitchen, holding cold water in your mouth for temporary relief, or unable to lie flat because pressure makes things worse, it is time to stop guessing and seek advice.
What symptoms mean I should not delay care?
Swelling is the symptom patients underestimate most often. They may think, “It is just a puffy gum,” when the deeper issue is an abscessed tooth. A localized bump on the gum can still be urgent, especially if it drains fluid, tastes bad, or comes and goes with pain. Fever, facial asymmetry, swollen lymph nodes under the jaw, and a foul taste in the mouth all raise concern for infection.
A knocked-out adult tooth is another situation where minutes matter. The best chance of saving the tooth comes when it is reimplanted quickly, ideally within about 30 minutes, though dentists still want to see the patient even if more time has passed. The same urgency applies to a tooth that has been pushed out of place or loosened by trauma.
Bleeding after an extraction or injury also deserves respect. A little oozing can be normal. Steady bleeding that soaks gauze repeatedly or resumes after appearing controlled should prompt a call. People often over-rinse, spit frequently, or disturb the clot without realizing it, which can worsen the problem.
What will happen when I call the office?
If you have never seen an Emergency Dentist before, the phone call can feel intimidating. It is usually much more straightforward than patients expect. The front desk or on-call provider will ask when the problem started, where the pain is located, whether swelling or fever is present, whether trauma occurred, and whether you are an established patient. They may also ask about medications, allergies, pregnancy, or significant health conditions such as diabetes, immune suppression, heart conditions, or blood thinners.
Be ready to describe the pain in plain language. Saying “upper right tooth, sharp when I bite, started yesterday, now my cheek feels swollen” is more helpful than simply saying “my whole mouth hurts.” If you can identify the general area, whether the pain is constant or triggered, and whether hot, cold, or chewing worsens it, that gives the office a better sense of urgency.
If the swelling is visible, some offices may ask you to send a photo. Photos are useful, but they do not replace an exam. Dental pain can refer to nearby teeth, the bite can hide cracks, and infections often behave differently than they look.
Will they treat the problem right away or just stop the pain?
That depends on the diagnosis and the condition of the tooth. In many urgent appointments, the dentist aims to do both, relieve pain and begin definitive treatment. If the source is clear and the situation allows, care may include draining an abscess, placing a temporary or permanent restoration, adjusting the bite, recementing a crown, beginning a root canal, extracting a non-restorable tooth, or stabilizing a traumatized tooth.
In other cases, the first visit is focused on immediate control, especially if swelling is significant, the area is difficult to numb because of active infection, or you arrive late in the day with a problem that requires more time than the schedule allows. Patients are sometimes disappointed when a dentist does not complete every step in a single visit, but there are sound reasons for that choice. An infected tooth may need staged care. A cracked tooth may need imaging and a follow-up discussion about whether it can be saved. A child or highly anxious adult may need sedation planning rather than rushed treatment.
The important thing is that the first emergency visit should move the situation forward. You should leave with a diagnosis or at least a strong clinical impression, a plan, and steps to control symptoms.
Will I need X-rays?
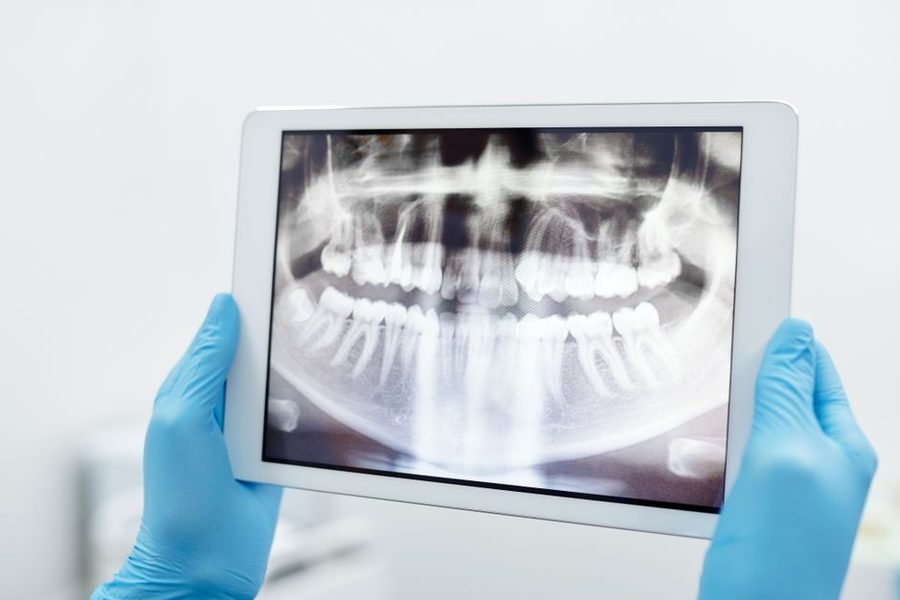
Very often, yes. Dental emergencies are notorious for hiding beneath the surface. A small cavity can develop into a large abscess at the root tip. A tooth that seems “just chipped” may have a fracture line extending deeper. A painful wisdom tooth can involve the surrounding gum tissue rather than the tooth itself. X-rays help determine the source, depth, and next best step.
First-time patients sometimes worry that taking an X-ray will delay treatment or increase cost unnecessarily. In urgent care, a focused dental radiograph is usually one of the fastest ways to avoid treating the wrong tooth or missing a condition that cannot be seen clinically. Dentists would rather spend a few extra minutes confirming the source than perform a procedure based on guesswork.
If you are pregnant, tell the office. Dental X-rays can often still be taken when necessary with appropriate shielding and judgment, but the team should know so they can tailor care.
What if I have a knocked-out tooth?
Handle it carefully and act fast. Pick the tooth up by the crown, the part you normally see in the mouth, not the root. If it is dirty, rinse it gently with milk or saline if available, or clean water for a few seconds if needed. Do not scrub it, and do not wrap it in tissue. If you can place it back in the socket correctly, do so gently. If not, store it in milk or keep it between the cheek and gum if the person is old enough to do so safely without swallowing it.
This is one of the few situations where immediate action at home can significantly improve the outcome. Time matters because the cells on the root surface begin to die when they dry out. Even when reimplantation is successful, the tooth may still need splinting and later root canal treatment, but quick handling improves the odds.
Baby teeth are different. A knocked-out primary tooth is generally not replanted because doing so may damage the developing permanent tooth underneath. Parents are often understandably alarmed, but the management is not the same as with an adult tooth.
Do antibiotics solve a dental emergency?
Not by themselves. This is one of the most persistent misunderstandings in urgent dentistry. Antibiotics can help control bacterial spread in certain infections, especially when swelling, fever, or diffuse involvement is present. What they do not do is remove the cause. If the problem is dead or dying tissue inside the tooth, a deep cavity, a crack, or trapped infection https://trevordzly832.tearosediner.net/emergency-dentist-advice-for-swelling-pain-and-infection around the root, the tooth still needs treatment.
Patients sometimes call hoping for “just an antibiotic” to get through the weekend. In some cases, the dentist may prescribe one as part of the short-term plan. In many others, antibiotics are not even the best first step. A localized toothache without swelling may not benefit from them at all. Overprescribing is not good medicine, and it does not spare the patient from the real treatment. It usually delays it.
A useful comparison is a splinter under the skin. Antibiotics may reduce some surrounding inflammation, but if the splinter stays in place, the irritation remains. Dentistry works much the same way.
How much does an emergency dental visit usually cost?
Costs vary widely by region, practice type, and what the visit includes. A straightforward exam with one or two focused X-rays may be relatively modest compared with actual treatment. If the visit leads to drainage of an abscess, placement of a sedative filling, extraction, or emergency root canal care, the total rises accordingly.
The more practical question for first-time patients is what to ask when they call. Ask whether the office charges a separate emergency exam fee, whether X-rays are included, and what forms of payment they accept. If you have insurance, ask whether they can estimate your portion. Estimates are not guarantees, but they help you prepare.
Emergency care sometimes feels expensive in the moment because it is unplanned. What people overlook is the cost of waiting. A small fractured filling that might have been repaired can progress to a fracture that requires a crown, root canal, or extraction. A cavity that hurt only with cold six months ago can become a weekend abscess. Early treatment is not only more comfortable, it is often less costly.
What should I bring to the appointment?
Most urgent visits run more smoothly when the basics are ready before you leave home. Patients in pain are understandably scattered, and that can slow registration and treatment.
Bring these essentials if you can:
- A photo ID, insurance card if you have one, and a form of payment.
- A list of medications, allergies, and major medical conditions.
- Any dental appliance involved, such as a broken crown, bridge, retainer, or denture piece.
- The knocked-out or broken tooth fragment, stored properly if applicable.
- A brief timeline of what happened, especially if trauma was involved.
If you are taking pain medicine, note the name, dose, and time of your last dose. That helps the dentist recommend safe timing for anything additional. If the patient is a child, bring the legal guardian who can consent to treatment unless the office has already confirmed another arrangement.
Will it hurt to be treated when the tooth is already inflamed?
This is one of the biggest fears first-time patients carry into the chair. The honest answer is that inflamed teeth can be harder to numb completely, but experienced emergency clinicians expect that and adjust. They may use supplemental anesthetic techniques, allow more time for the anesthetic to work, or choose an initial treatment approach that reduces pressure and pain before doing more.
People often arrive apologizing for being “bad at the dentist,” when what they really mean is that they are frightened because they waited until the pain became intense. That is common, not unusual. A good Emergency Dentist does not expect you to be relaxed on arrival. The goal is to get you from crisis mode into manageable territory as safely and efficiently as possible.
If you have had difficulty getting numb in the past, say so early. That history matters. Likewise, tell the dentist if local anesthetic tends to wear off quickly, if you are very anxious, or if you have fainted during previous procedures. None of that is embarrassing. It is useful clinical information.
What if I am pregnant or have a medical condition?
Urgent dental care can often be provided safely during pregnancy, and ignoring infection is usually the greater risk. Dentists may modify imaging, medication choices, and timing based on the trimester and the nature of the problem. The same principle applies to patients with diabetes, heart conditions, recent joint replacements, bleeding disorders, or immune suppression. The emergency still needs attention, but the care plan may be tailored more carefully.
Patients taking blood thinners should mention that before any procedure that might involve bleeding. It does not always prevent treatment, but it affects planning. People with poorly controlled diabetes are also more prone to severe or persistent oral infections, and healing may be slower. Those details help the dentist judge urgency and coordinate with a physician when needed.
Can a tooth always be saved?
No, and that is hard to hear in the middle of an emergency. Teeth can become non-restorable because decay extends too far below the gumline, a crack reaches into the root, bone loss is severe, or trauma has compromised the supporting structures beyond repair. In those cases, the most responsible recommendation may be extraction, not because it is the easiest option, but because preserving a tooth at all costs can lead to repeated pain, repeated expense, and eventual failure anyway.
There is real judgment involved here. Some borderline teeth can be stabilized for a time, especially if the patient needs to get through travel, a major event, or a period when definitive treatment is not immediately possible. Temporary solutions have value when used honestly. The key is understanding whether the temporary fix is buying useful time or merely postponing an unavoidable outcome.
Patients appreciate straightforward language here. “We may be able to save this, but the prognosis is guarded,” is very different from “No problem, we can patch it,” when the tooth is actually split. Good emergency care balances hope with realism.
What happens after the visit?
Most emergency appointments are the beginning of treatment, not the end of it. Even when you leave feeling dramatically better, follow-up is often necessary. A temporary filling may need replacement. A tooth opened to relieve pressure may still need root canal therapy or a crown. A draining abscess may settle down, but the source must still be addressed. An extraction site needs monitoring. A traumatic injury may require repeat X-rays over time.
This is the point many first-time patients miss because once the pain recedes, the urgency feels gone. Clinically, however, the problem may simply be controlled rather than resolved. The difference matters. Teeth that felt “fixed” after an emergency patch often return months later in worse condition because the patient understandably assumed the crisis visit completed the job.
If you are given instructions about diet, rinsing, medication timing, or follow-up dates, take them seriously. Soft foods for a few days, avoiding chewing on the affected side, finishing prescribed medication appropriately, and returning when advised can make the difference between recovery and relapse.
How can I lower the chances of needing another emergency visit?
Many dental emergencies cannot be predicted. People fall, grind their teeth in their sleep, crack a cusp on an olive pit, or develop pain from a tooth that had no obvious warning signs. But a large share of urgent visits are tied to delayed routine care. Fillings that have worn down for years, broken crowns that were “fine unless I chewed there,” and gum infections that bled for months before suddenly swelling are common stories in emergency schedules.
Regular exams do not prevent every crisis, but they catch a lot of problems while they are still smaller, cheaper, and more comfortable to manage. Night guards for clenching, replacing large failing fillings before they fracture the tooth, treating decay early, and addressing wisdom tooth issues before infection develops all help.
If there is one takeaway first-time patients benefit from most, it is this: dental emergencies rarely improve by being ignored. Pain may fluctuate, swelling may temporarily subside, and a chipped edge may stop catching your tongue, but the underlying cause typically remains. Reaching out early usually expands your options. Waiting narrows them.
The first urgent dental visit is unfamiliar only until you have been through it once. After that, most people are surprised by how procedural and practical it is. The office asks focused questions, identifies the source, controls the immediate problem, and outlines what comes next. That clarity alone often brings relief before treatment even begins. When the problem is handled promptly, many emergencies become manageable detours rather than lasting setbacks.
Smyle Dental Bakersfield
2016 E St, Bakersfield, CA 93301, United States
+16614939040
FAQ About Emergency Dentist
What counts as a dental emergency?
Severe tooth pain, facial swelling, uncontrolled bleeding, a knocked-out or displaced tooth, and significant dental trauma may need prompt assessment. Trouble breathing or rapidly increasing swelling requires urgent medical help.
What should I do if a permanent tooth is knocked out?
Handle the tooth by the crown rather than the root, keep it moist, and contact a dentist immediately. Fast treatment can improve the chance of saving the tooth.
Can an emergency dentist treat severe tooth pain the same day?
Same-day care may be available depending on the cause and schedule. The dentist will examine the area, may take digital X-rays, and recommend treatment based on the diagnosis.
Should I go to the emergency room for dental swelling?
Seek urgent medical care for trouble breathing, difficulty swallowing, rapidly spreading facial swelling, or other severe symptoms. A dentist can assess the underlying dental cause and provide appropriate follow-up care.